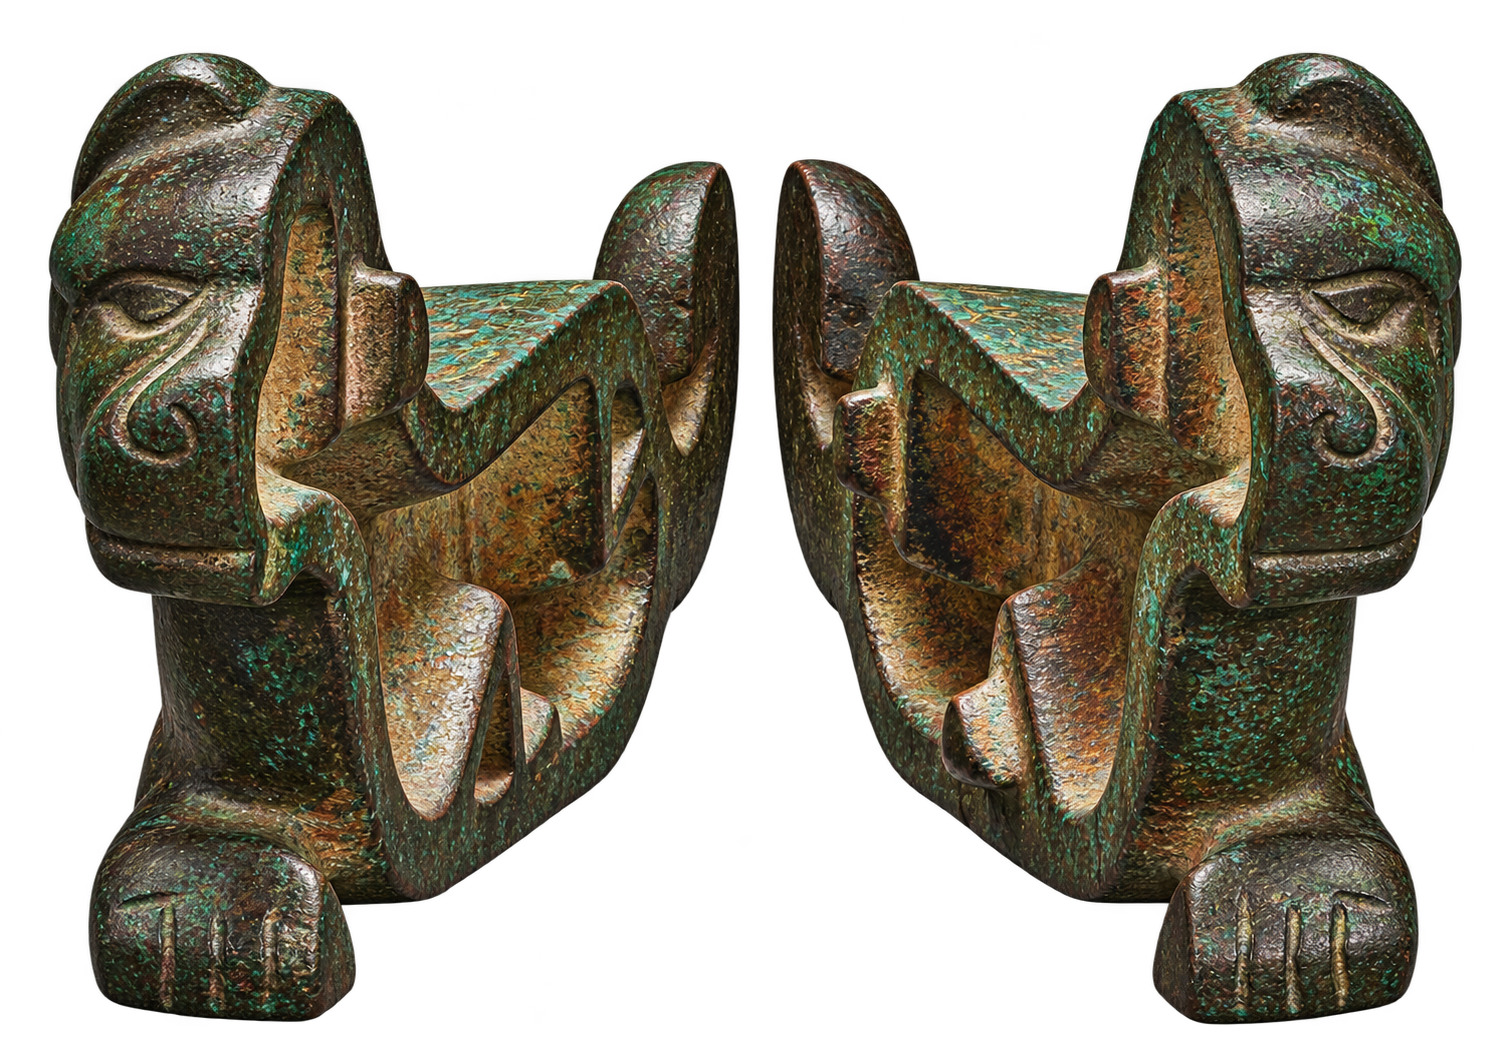# COPPER TIGER — Defence healthcare
How should Defence maintain patients’ lifelong primary (GP) records of care in line with applicable NHS conventions and standards, preserving continuity and supporting record transfer from and to NHS general practice when Defence care arrangements begin and end?
In parallel, how should Defence develop a complementary internal Defence Shared Care Record (DShCR) that brings information from multiple source systems into a contiguous, longitudinal view, supports business continuity, and enables appropriately governed information access and sharing across Defence healthcare and occupational health-led military medicine?
COPPER TIGER defines an evolving programme and architecture. It covers Armed Forces and civilian patients within Defence healthcare and the whole operating model across Firmbase, Overseas and Operational (MARITIME, LAND and AIR) environments. All healthcare purposes remain in scope, as do NHS, devolved, overseas, allied and contracted interfaces. [SRC-211](https://copper-tiger.pages.dev/sources/index.md#src-211) [SRC-219](https://copper-tiger.pages.dev/sources/index.md#src-219)
**Leading architectural principle:** Maintain the continuing primary record of care to applicable NHS conventions and standards, alongside a complementary, appropriately governed **Defence Shared Care Record (DShCR)**. The DShCR brings fuller information from contributing clinical services and supporting tools into shared use within Defence, with integration to national and regional services. This principle will be tested and developed during programme definition. [SRC-212](https://copper-tiger.pages.dev/sources/index.md#src-212) [SRC-219](https://copper-tiger.pages.dev/sources/index.md#src-219)
The proposed DShCR would provide a comprehensive, primarily read-only overview across multiple source systems, with authorised access to their complete clinical source records through that view. Contiguous describes a connected presentation across sources; longitudinal describes continuity over time. Coverage, freshness and access conditions must remain clear: a connected view does not establish that every source is available or every entry universally accessible. Source systems would retain their originating records and correction responsibilities. [SRC-220](https://copper-tiger.pages.dev/sources/index.md#src-220)
An associated **Integration Platform (IntP)** would coordinate information exchange and publish–subscribe notifications between the DShCR, independent source systems and other supporting tools. These flows would operate in both directions, including back to specialist source systems. An Enterprise Master Patient Index (EMPI) would support patient matching and shared demographics. A Healthcare Provider Directory (HPD) would supply provider identities, profiles and relationships that inform access and routing. [SRC-220](https://copper-tiger.pages.dev/sources/index.md#src-220)
Exchange of core clinical information—including **conditions, medications, vaccinations and allergies**—would support consistent information use and **clinical decision support systems (CDSS)** within specialist source systems. Information authority, provenance, currency, corrections and reconciliation would need defined rules. [SRC-220](https://copper-tiger.pages.dev/sources/index.md#src-220)
Business continuity options would include retained information, consultation capture and subsequent reconciliation, with their scope and implementation to be determined. [SRC-220](https://copper-tiger.pages.dev/sources/index.md#src-220)
**The Copper Tiger:** The image recalls a Chinese tiger tally (*hufu*), a bronze token divided into matching halves. One was held by the ruler, the other by a military commander; bringing them together verified the authority of orders to deploy troops. [SRC-042](https://copper-tiger.pages.dev/sources/index.md#src-042)
## Read the argument in order
1. [Programme definition](https://copper-tiger.pages.dev/programme-definition/index.md): the evolving problem, scope, decision sought and outcomes.
2. [Foundations](https://copper-tiger.pages.dev/foundations/index.md): records, systems, information, work, governance and assurance.
3. [Defence context](https://copper-tiger.pages.dev/defence-context/index.md), [primary record](https://copper-tiger.pages.dev/primary-record/index.md) and [operating model](https://copper-tiger.pages.dev/operating-model/index.md): care continuity and responsibilities.
4. [Internal Defence architecture](https://copper-tiger.pages.dev/architecture/index.md): capabilities, purpose boundaries, work states and disconnected operation.
5. [National and regional integration](https://copper-tiger.pages.dev/national-regional-integration/index.md): external services, public evidence and open participation questions.
6. [Information flows](https://copper-tiger.pages.dev/information-flows/index.md), [governance](https://copper-tiger.pages.dev/governance/index.md) and [NHS reference model](https://copper-tiger.pages.dev/nhs-reference-model/index.md): detailed patterns and evidence.
7. [Project status](https://copper-tiger.pages.dev/project/status/index.md), [discovery](https://copper-tiger.pages.dev/validation-queue/index.md) and [evidence matrix](https://copper-tiger.pages.dev/evidence-matrix/index.md): what is proposed, supported and unresolved.
## A continuity example
```mermaid
flowchart TB
accTitle: Proposed lifelong GP record journey
accDescr: One continuing GP record moves from NHS general practice through Defence primary healthcare and back to NHS general practice. This is a future design objective, not a claim of live transfer capability.
A["NHS general practice"] --> B["Defence primary healthcare"]
B --> C["NHS general practice"]
```
This selected journey illustrates continuity when primary-care providers change. Civilian and military care may also occur concurrently, and each source retains its own account. Record transfer, correspondence, shared access and clinical handover remain separate.
## How to read this wiki
| Layer | What this edition says |
|---|---|
| **Public evidence** | Supports bounded, dated statements. |
| **Proposed direction** | Sets hypotheses and future requirements. |
| **Discovery questions** | Identify unresolved decisions and missing evidence. |
The definition is future-looking and supplier agnostic. Source metadata preserves historical provenance without endorsing products. Neither owner direction nor a published supplier capability establishes organisational approval or Defence deployment.
Use [sources](https://copper-tiger.pages.dev/sources/index.md), [terms](https://copper-tiger.pages.dev/terms/index.md), [research log](https://copper-tiger.pages.dev/log/index.md) and the [knowledge graph](https://copper-tiger.pages.dev/graph/index.md) for reference. The previous wiki is preserved as the first major release; see [release history](https://copper-tiger.pages.dev/project/releases/index.md). The [LLM entry](https://copper-tiger.pages.dev/llm-wiki/index.md) governs maintenance.